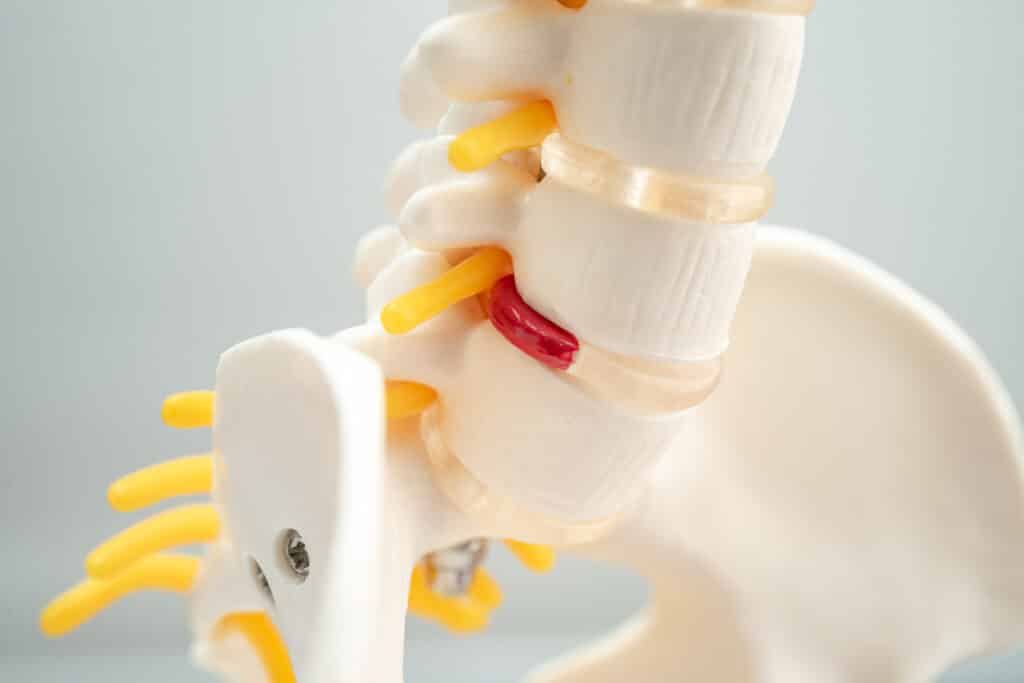
Shoulder pain at night is pain that flares up or wakes you once you lie down, even when the shoulder feels manageable during the day. It is one of the most common reasons people seek care for a shoulder. Night shoulder pain is often linked to rotator cuff tendinopathy or tears, bursitis, impingement, shoulder arthritis, biceps tendon irritation, frozen shoulder or calcific tendinitis, and sometimes the source is a pinched nerve in the neck.
This guide explains why shoulder pain gets worse at night, which sleeping positions tend to help or hurt, how to tell shoulder pain from pain coming from the neck, what treatment usually involves, and which symptoms need prompt medical attention. It also covers common myths about sleeping on the "good side," lying flat on your back, and buying a new pillow or mattress.
Your shoulder did not get worse between dinner and bedtime. What changed is everything around it. The position of your arm, the pressure on the joint, the amount of noise competing for your attention, and even your own hormones all shift once the lights go off. Some of those shifts matter more than others.
What we usually find: position is the trigger, not the cause. A healthy shoulder may feel stiff after hours in one position, but it does not reliably wake you night after night. Pain that shows up on schedule points to tissue that is already irritated.
Several shoulder problems are known for this pattern: rotator cuff tendinopathy and tears, bursitis, impingement-type pain, shoulder arthritis, biceps tendon irritation, and frozen shoulder. During the day they feel different from each other. At night they can all feel much the same to you, which is why the internet's one-size answer tends to disappoint.

Frozen shoulder, also called adhesive capsulitis, is swelling and tightening of the capsule that wraps the joint. It often starts as a deep ache that is worst at night, with stiffness building over weeks. It turns up most often between about 40 and 60, more often in women, and it is strongly linked with diabetes, thyroid disease, and any stretch of time when the arm was kept still. The condition usually runs months to a couple of years, and treatment is aimed at shortening that course and making it easier to live through. If your reach is shrinking as well as hurting, have it examined.
What we usually find: the opposite side has its own problem. Roll away from the painful shoulder and that arm tends to drop forward across your body, unsupported, with the whole weight of the limb pulling on tendons that are already unhappy. People wake up confused, because they did the one thing everyone told them to do.
Give the arm something to rest on. A pillow hugged against your chest keeps the top arm level with the shoulder instead of sagging toward the mattress, and it blocks you from rolling onto the painful side in your sleep. Some people need a second pillow behind the back for the same reason.
What we usually find: back sleeping is a reasonable starting point, but flat on a mattress lets the arm fall backward and the front of the shoulder stretch open. That position can stir things up more than people expect, especially with cuff pain.
Two adjustments help more than switching sides does. Put a small pillow or folded towel under the upper arm and elbow so the arm sits slightly forward of the body rather than dropping back. Then try sleeping propped up instead of flat, on a wedge or stacked pillows or in a recliner, which brings back some of the gentle pull the shoulder loses when you're horizontal.
Sleeping with the arm overhead or tucked under the pillow is the position most worth breaking. If you have had shoulder surgery, your surgeon's instructions come first, and those often include a period of sleeping reclined or in a sling.
What we usually find: support changes how loudly the problem speaks, not whether it exists. A pillow that keeps your head level with your spine and an arm that is not dangling will often buy you a few more hours of sleep. Neither one heals a torn tendon or a stiff capsule.
Use the setup to get through the next few weeks while you work on the shoulder itself. If you're still rearranging pillows a month later with no progress, that is worth bringing to an exam.
What we usually find: sudden, intense shoulder pain with no injury behind it often turns out to be calcific tendinitis. Calcium deposits build up quietly inside a rotator cuff tendon and frequently cause little trouble for months. The crisis comes when the body starts breaking the deposit down.
That breakdown phase is inflammatory. The pain can arrive overnight and feel far out of proportion to anything you did. People describe being unable to lie on that side at all, and some head to an emergency room convinced something ruptured. An X-ray or ultrasound usually settles the question quickly. The flare does tend to calm down on its own, and there are ways to move things along faster, including anti-inflammatory medication, a cortisone injection, and image-guided treatment such as ultrasound-guided needling and lavage, where the deposit is broken up and washed out through a needle.
What we usually find: a fair share of shoulder pain is actually referred from the neck. An irritated nerve root in the cervical spine can send pain into the shoulder, the outer arm, or the hand, and it tends to act up at night when your head settles into a position that narrows the space the nerve travels through. Neck and shoulder problems can also exist at the same time in the same person, which is why we examine both when the picture is unclear.
Leans toward the neck
Leans toward the shoulder joint
These lists overlap on purpose. Sorting it out is what an exam is for.
What we usually find: the traffic runs both ways. Research on sleep and pain keeps showing that short or broken sleep lowers pain thresholds and weakens the body's own pain-calming pathways. So the shoulder that kept you up is likely to hurt more the next day because of it.
That loop is worth taking seriously, and it is a fair reason to treat night pain as a real medical complaint rather than an inconvenience. Protecting sleep is part of the treatment, not a reward for finishing it.
Most shoulder night pain gets better without surgery. Care usually starts with calming the irritation down, then rebuilding the muscle support around the joint so the shoulder can handle normal loads again. The order matters more than people expect, and these pieces tend to work better together than any one of them alone.
Surgery enters the conversation when non-surgical care has had a fair trial, or when an exam points to a tear that is unlikely to settle on its own. Timelines vary from person to person, and any estimate we give you is a range rather than a promise.
Go to emergency care if shoulder pain comes with chest pressure, shortness of breath, cold sweats, nausea, or lightheadedness. Heart-related pain is classically felt on the left and can spread to the jaw, the neck, or both arms. Women and people with diabetes may have less typical symptoms, so judge the whole picture rather than one detail. The same urgency applies to severe belly pain, fever, or yellowing of the skin or eyes alongside shoulder or shoulder blade pain. A shoulder that is hot, red and swollen with a fever can mean a joint infection and needs to be seen the same day. Arm weakness that keeps getting worse, clumsy hands, a change in how you walk, or new bowel or bladder trouble can point to pressure on the spinal cord in the neck, and those belong in the urgent category too.
Call within a few days if the arm has gone weak or you cannot raise it after a fall or a sudden pull. That pattern can mean a fracture, a dislocation, or a fresh rotator cuff tear, and with some tears an earlier repair leads to a better result. Night pain with no clear explanation also deserves a prompt call if you have a history of cancer, you have lost weight without trying, or you're waking up with night sweats.
Most night pain is not an emergency, but it still earns a closer look when it keeps coming back. Pain that has outlasted a few weeks of careful sleeping and sensible activity changes usually has a cause worth naming. Call during office hours and schedule an exam if any of the following sound like your shoulder.
No, and for many people with cuff pain or frozen shoulder it is the first comfortable night in a while. Treat it as a bridge while the shoulder is being treated rather than a permanent arrangement, and mention it at your visit so we know how much the pain is running your days.
Either can help, depending on how the shoulder feels. Heat suits a stiff, tight shoulder, and ice suits one that feels hot and swollen. Keep it to roughly 15 to 20 minutes at a time and always put a cloth between the pack and your skin. If you have diabetes, neuropathy, or poor circulation, be extra careful, since you may not feel a burn or a cold injury starting. Try one approach for several nights before deciding it did not work.
It probably does hurt during the day, at a level that movement and distraction cover up. Lying down removes the gentle pull gravity provides, adds pressure if you roll onto that side, and hands the ache your full attention.
Gentle range of motion can help a stiff shoulder settle, but hard end-range stretching often stirs up an irritated one and makes the next few hours worse. If stretching consistently increases your pain, stop and let us look at it before you keep pushing.
Start with the easy changes tonight: support the arm, avoid the painful side, and try sleeping propped up rather than flat. If you're still being woken after a few weeks, or if weakness or stiffness is creeping in, bring it to us. We will examine the shoulder, check the neck when the pattern calls for it, and build a plan that gets you back to sleeping through the night.
This article is for general education and is not a substitute for medical advice. Talk with your OrthoNJ provider about your specific symptoms.
If shoulder pain is costing you sleep, schedule an exam with an OrthoNJ orthopaedic specialist near you.
This treatment info is for informational purposes only. Treatment and recovery vary person to person, and you should consult with your treating physician and team for details on your treatment and recovery process.
Contact one of OrthoNJ's locations spread out through all of New Jersey.